HOW RUSH REALLY FEELS ABOUT SANDRA FLUKE

Sunday, July 23, 2006

Guidelines

The American College of Cardiologists and American Heart Association have posted the most recent guidelines for Coronary Artery Bypass Graft Surgery at this website.

The 89-page document makes interesting reading.

Pay particular attention to Part III, "Predicted Outcomes."

Here are some scary facts about CABG:

  • Neurological abnormalities after CABG are a dreaded complication. The reported incidence ranges from 0.4% to nearly 80%, depending on how the deficit is defined (46–48). Neurological derangement after CABG has been attributed to hypoxia, emboli, hemorrhage, and metabolic abnormalities (49,50). Despite the many advances made in cardiac surgery, postoperative stroke remains a problem.

  • Deep sternal wound infection has been reported to occur in 1% to 4% of patients after CABG and carries a mortality rate of nearly 25% (57,58). Studies have consistently associated obesity and reoperation with this complication, while other risk factors such as use of 1 or both IMAs, duration and complexity of operation, and the presence of diabetes have been reported inconsistently.

  • The first major multicenter study of renal dysfunction after CABG surgery has recently been published (67). This study of 2,222 patients who underwent myocardial revascularization with CPB defined postoperative renal dysfunction (PRD) as a postoperative serum creatinine level of ≥2.0 mg/dL or an increase in the serum creatinine level of ≥0.7 mg/dL from preoperative to maximum postoperative values. PRD occurred in 171 (7.7%) of the patients studied; 30 of these (18%, or 1.4% of all study patients) required dialysis. The mortality rates were 0.9% among patients who did not develop PRD, 19% in patients with PRD who did not require dialysis, and 63% among those who required dialysis.

  • CABG is potentially indicated for 2 symptom-based indications: to alleviate symptoms of angina pectoris over and above medical therapy and to reduce the incidence of nonfatal outcomes such as MI, CHF, and hospitalization. [You must ask yourself why your doctor doesn't want to treat your angina with medicine before using the "big guns of CABG.]

  • The operative mortality of reoperations for CABG is distinctly higher than the mortality of first-time operations. Reoperative mortality increases with the urgency or severity of symptoms, age >65 years, <1> and low EF (34)(Table 15) (553–555). The highest risk seems to be associated with a short time interval between the first operation and the subsequent need for reoperation. Christenson et al (34) group of patients who underwent reoperation <1> their first CABG. This figure was compared with an 8% mortality in those patients who had an operation-free time of >1 year. The presence of diabetes was greater in the group undergoing operation in <1> reported a reoperative mortality risk of 18% in a

  • The second important indication for CABG, after relief of symptoms, is prolongation of life. The randomized trials of CABG versus medical therapy have defined patient subsets whose survival is enhanced. These patients tend to be those with advanced coronary disease: notably left main disease and triple-vessel disease (or double-vessel disease including a proximal LAD stenosis) combined with LV dysfunction.
This is an interesting document that has thousands of links to references. It is probably worth studying, if you do so with a grain of salt, realizing the economic considerations of CABG versus Medical treatments.

The last post quoted Dr. Thomas Rodaman, Director of the Kansas University Cardiac Scanning Center. I think it is very approprop to highlight some statements he and another physician made in the article. The other doctor is David Marks of the cardiology department of the Medical College of Wisconsin.

First, Dr. Rodaman:

"We have a lot of patients who would benefit but decide against it because of the out-of-pocket costs," he said. "I think what insurers are afraid of is physicians will use it as a screening test inappropriately for everybody and they'll be flooded with claims."

Insurance companies and HMOs have done more to cause America's health care to deteriorate than any other entity in the health care delievery profession. People die in the United States every day because doctors try to keep the cost of care down as low as possible and also because many can't afford the high premiums it takes to be adequately insured.

Now Dr. Marks:

"How things are applied isn't always dictated by science," he said. "Medical opinion is like a big ship; once it is moving in one direction, it's hard to steer it in a different direction."

No truer words have been spoken, especially when it comes to angiograms and CABGs. The CABG has never beed approved by any governmental agency after a double-blind study, as is the normal process. Angiograms are not accurate. (See Dr. Wayne's website & books) Insist that you are allowed a second opinion from a noninvasive cardiologist if your doctor tries to scare you into an angiogram and/or CABG.

64 Slice CT Scan

Many parts of this story validate what noninvasive cardiologist have felt for a long time, too many people undergo Coronary Artery Bypass Graft Surgery. Perhaps in time, the 64-Line CT will replace the angiogram. For now, implore insurance companies to start covering it as a billable cost. It is a lot less expensive than a CABG


By Alan Bavley

McClatchy Newspapers

(MCT)

KANSAS CITY, Mo. - High cholesterol. High blood pressure. Years of smoking. It's not surprising that a doctor told Stephen Matthews to get his heart checked.

What's really amazing is how Matthews had it done.

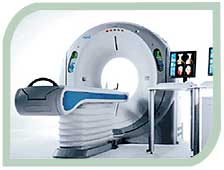
For about 10 seconds, Matthews lay still as a computed tomography scanner took X-ray pictures of his heart. Not just any CT scanner, but a new 64-slice CT scanner, one of the hottest pieces of medical hardware on the market.

There on a computer screen at the University of Kansas Hospital was Matthews' heart in vivid colors, every detail of muscle and arteries and surrounding anatomy rendered in almost photographic detail.

This is medical technology on steroids. It's expensive - as much as $1,000 to $2,000 per procedure - it produces gee-whiz results, and it is almost inevitable that it will be widely used before researchers can fully judge its effectiveness.

Hundreds of hospitals and clinics have snatched up the $1.8 million scanners since 2004, when the Food and Drug Administration approved them for use.

For the medical industry, the adoption rate is something akin to the way consumers embraced DVD players.

Some doctors already have expressed concern that the use of 64-slice scanners may be outrunning medical knowledge about the devices.

The scans can detect tumors and other anomalies so minute that doctors are unsure whether they even need to treat them. And used inappropriately, scans would needlessly expose patients to substantial doses of radiation.

"It's exciting. There's a lot of expectation. But you want to be careful about how you use it," said radiologist Udo Hoffmann of Harvard University Medical School.

Experts say 64-slice CT has the potential to revolutionize many fields of medicine, from assessing the injuries of trauma patients to finding tumors to plotting surgeries.

But the most radical transformation may come in the way doctors evaluate patients such as Matthews for coronary heart disease.

"Cardiac CT is the killer application," said Elliot Fishman, a 64-slice CT scanner expert at Johns Hopkins University. "With that, we change how medicine is practiced."

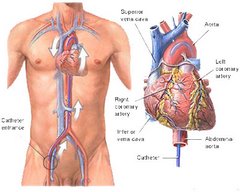
Until 64-slice CT, the only certain way to tell whether a patient's coronary arteries were blocked was with a costly, invasive technique called angiography. In it, doctors snake a catheter from a blood vessel in the groin up to the heart, then inject dye into the coronary arteries and watch the results on an X-ray screen.

Nearly 1.5 million patients undergo angiography in the U.S. each year. Many discover problems that may require interventions such as bypass surgery. But in nearly a third of the cases, the results turn out to be normal.

Doctors hope that many of these relatively healthy patients can be ruled out if they get CT scans first.

That would save patients from the cost of angiography - which averages nearly $10,000 at the University of Kansas hospital, for example. Patients also would avoid the small, but real, risks of angiography: a blood clot or torn artery.

Patients still would have to undergo angiography if their CT scans do not show that their arteries are clear.

"You get a lot of people with chest pains, short of breath. We've always wanted to do noninvasive coronary artery imaging, but we didn't have the tools to do it," said radiologist Louis Wetzel, who runs KU's heart scan program with cardiologist Thomas Rosamond.

In a fraction of a second, the new CT scanners take 64 X-ray images, each a separate "slice" of the body as thick as about five pieces of notebook paper. That is several times the number of images taken by the 4- and 16-slice CT scanners that were state-of-the-art just a few years ago.

After the scanner has made multiple passes around the patient's body, computers assemble the data into images of the heart's exterior and interior.

The higher resolution and faster speed of the new scanners make it possible for the first time to view a beating heart without blurring.

Some studies have found that 64-slice CT can rule out coronary heart disease with 99 percent accuracy.

"Neither of us in our lifetimes thought this would happen," Wetzel said. "Now we can see tiny little vessels. We're really amazed."

Wetzel and Rosamond use the scanner when patients with chest pains or risk factors for heart disease have ambiguous results on another key screening tool, a treadmill stress test.

The results can be unpredictable. A 67-year-old man, a healthy-looking avid tennis player, turned out to have a severely blocked artery; a 73-year-old man with diabetes had a normal scan.

Doctors gave Matthews, a banker from LaCygne, Kan., in his early 60s, the option of angiography or CT. A scan made more sense, he said.

"If I could go through this deal without anyone cutting on me, it will be all right," Matthews said.

When it was over, Matthews was relieved. The scan showed no blockages in his coronary arteries. "Nothing unusual for an old (guy) like me," he said.

Rosamond and Wetzel have been getting urgent requests from KU emergency-room doctors to evaluate their heart patients.

Chest pains account for as many as 8 million trips to emergency rooms every year in the U.S. Nearly half these patients are admitted overnight to hospitals to undergo tests and angiography. Many of these hospitalizations turn out to be unnecessary.

So far, the KU doctors don't think they have had enough experience with the scanner to use it on ER patients.

"The stakes are huge - if you decide wrong and send them home with a heart attack, that's a million-dollar lawsuit," Rosamond said.

Other hospitals are testing the scanner in their ERs.

At the Hospital of the University of Pennsylvania in Philadelphia, low-risk patients who come to the ER with chest pains get preliminary tests and a CT scan. If the results are negative, the patients are discharged.

About 85 percent to 90 percent of patients who have gotten the scans have been able to go home, said radiologist Harold Litt.

Researchers check on these patients 30 days later.

"Nobody we've said was negative has ended up having a cardiac problem," Litt said. "That's the sort of thing that makes physicians more comfortable."

CT scans may be fine for low-risk patients who come in through the ER, said cardiologist David Marks of the Medical College of Wisconsin, one of the first doctors to use a 64-slice scanner.

Higher-risk patients who are destined for bypass surgery or angioplasty to open blocked arteries still need the demonstrated reliability of angiography to determine the extent of their disease.

"We've yet to really prove in all patient populations the diagnostic effectiveness of this (CT) test," Marks said.

That lack of evidence is holding back insurance companies' approval of 64-slice CT scans.

Medicare is leaving coverage decisions up to the local insurance companies that process its claims.

Most private insurance companies cover the scans only on a case-by-case basis, said Rosamond of KU. Many patients are being turned down.

"We have a lot of patients who would benefit but decide against it because of the out-of-pocket costs," he said. "I think what insurers are afraid of is physicians will use it as a screening test inappropriately for everybody and they'll be flooded with claims."

But it could be hard to keep the floodgates closed. Widespread adoption of 64-slice CT heart scans is likely to happen before all the evidence is in, said Hoffmann of Harvard.

"How things are applied isn't always dictated by science," he said. "Medical opinion is like a big ship; once it is moving in one direction, it's hard to steer it in a different direction."

Wednesday, June 14, 2006

Healthboards.com

Those few people who have been following my CABG posts on a small health-oriented site called Healthboard.com, may have noticed my posts disappeared. I also have been banned from the site. I am not certain whether my banishment is temporary or is of the lifetime variety. Anyone interested in the latest information about noninvasive treatments for Coronary Artery Disease or Unstable Angina can still read and reply to comments here, where there never will be any censorship

You also can contact my cardiologist at the address, phone number and URLs listed below:


Dr. Howard Wayne
The Noninvasive Heart Center
2550 Fifth Avenue, Suite 706
San Diego, California 92103
(619) 544-0200
www.heartprotect.com

Monday, June 12, 2006

Lifestyle Changes Endorsed by Medicare

Medicare will reimburse heart patients for two wellness programs that focus on wholesale changes. Supporters see the move as a shift toward proactive care.

By Hilary E. MacGregor
Times Staff Writer

June 12, 2006

LIFESTYLE changes can boost the health and well-being of heart patients, proponents of such programs have long said. Now Medicare has acknowledged that as well.

The federal insurance program will now pay for the intensive cardiac rehabilitation plans created by preventive health guru Dr. Dean Ornish and mind-body medicine pioneer Dr. Herbert Benson — the first time the federal government has agreed to reimburse consumers for specific lifestyle intervention programs.

"This exciting breakthrough could change the face of medical care," said Ornish in a statement.

He and Benson have been working for years to obtain Medicare reimbursement for their cardiac wellness programs because it's seen as a critical first step to making their programs more widely available — and getting other insurance providers to pay for them as well.

Both have conducted clinical research demonstrating that comprehensive lifestyle changes — including support groups; good nutrition and low-fat diets; exercise; and stress management, such as yoga, meditation or deep breathing — may begin to reverse even severe coronary heart disease without drugs or surgery.

Ornish's Program for Reversing Heart Disease is offered at eight sites in Pennsylvania and at five medical centers in West Virginia. At least one private insurer in each state already has agreed to cover the programs in those states.

Cardiac wellness programs by Benson, who more than 25 years ago wrote the groundbreaking "Relaxation Response," are offered in Indiana, Rhode Island, Tennessee, Washington and Virginia.

Considered by many to be the father of meditation in this country, Benson has shown that 10 minutes of meditative technique a day can increase concentration and counteract the harmful effects of stress, such as high blood pressure and strokes.

His Cardiac Wellness Program combines these stress reduction techniques with nutrition, cognitive restructuring and exercise to lower cholesterol and blood pressure. Patients report fewer symptoms of chest pain.

Medicare, however, will not cover enrollment in the programs for as long as both centers frequently recommend. Instead, it will guarantee coverage for 36 sessions within an 18-week period, with a possible extension to 72 sessions for 36 weeks. The final details of how much will be covered are still under negotiation, Ornish said.

Although Medicare already pays for some cardiac rehabilitation programs, officials hailed the inclusion of both programs as an important shift toward preventive rather than rehabilitative medicine.

As of March, the definition of who can take advantage of the cardiac rehab benefit under Medicare has been expanded from conditions such as acute myocardial infarction (heart attack) and coronary artery bypass graft to include patients with less severe heart conditions, such as valve replacement.

"The programs of Dr. Ornish and Dr. Benson focus on a prevention model," said a spokesperson with the Centers for Medicare and Medicaid Services. "Now we are going to take even individuals with mild cardiovascular disease and show them how to ameliorate it or reverse it to avoid more serious disease."

Although the details of coverage have not been finalized, doctors who run similar lifestyle intervention programs to treat and prevent heart disease supported the move.

"It is just phenomenal that Medicare has decided to cover these programs since Medicare sets the precedent for all of the other insurance companies," said Dr. Mimi Guarneri, a cardiologist who co-founded and runs the Scripps Center for Integrative Medicine in La Jolla.

"What's really important is this is truly shifting the paradigm of healthcare from focusing on chronic disease to focusing on prevention."

L.A. Times

Friday, June 09, 2006

Yet Another Physician Decries Unnecessary CABG

Coronary Angioplasty Indications
by Ron Kennedy, M.D., Santa Rosa, California

When to have invasive procedures and when not — what your doctor may not tell you.

The past 20 years has seen a proliferation of bypass surgery and angioplasty, in spite of strong scientific evidence that neither may be helpful in the long run for the overwhelming majority of patients. In general, the only reason for the one million such procedures each year is the high number of working cardiologists and cardiovascular surgeons in the medical community and the extremely high profitability of these procedures, around $70,000 for a bypass and $30,000 for an angioplasty.

The landmark CASS Study (stands for Coronary Artery Surgery Study) in 1984 demonstrated the irrelevance of bypass surgery and angioplasty to survival after the diagnosis of coronary artery disease is made. Analysis of outcome in 780 patients demonstrated no statistical difference in survivability between patients who both went to surgery and were treated medically and patients who were treated medically without surgery. Neverhteless, this extremely well documented study is generally ignored by doctors who do these procedures and never mentioned to patients who they consider candidates for bypass or angioplasty.

"Blockages," as reported from angiography are not an accurate reflection of blood flow according to a 1984 study published in the New England Journal of Medicine. No correlation between blockage and blood flow means the angiogram is worthless for gauging degree of blockage. (2)

If "blockages" are visible on angiogram, this does not mean bypass surgery or angioplasty should be done, since blood flow does not correlate with these images. What this study can tell you is if you have some plaque formation. However, the important item is blood flow. What does correlate with blood flow is the "ejection fraction," that percentage of the blood the left ventricle can eject from its volume at full expansion. For example, if the heart can empty ½ the volume it contains before contraction, the ejection fraction is said to be 50%.

If a cardiologist recommends angiogram (catheterization), the chances are it is not needed by the standards of the AMA. Ask your doctor to determine the ejection fraction and if it is 40% or better, decline the angiogram because your pump is healthy enough that whatever the results of angiogram, no surgery is advisable according to AMA guidelines. Why place yourself at the risk of death (1-2% for angiogram and 5% for bypass) if your pump is working?

According to the AMA the indications for bypass surgery are:

  1. when the left main coronary artery is blocked,
  2. when the patient has severe anginal pain which is unresponsive to all other therapies,
  3. when there is evidence of blockages in three coronary arteries and the ejection fraction is below 40%.

In these cases surgically treated patients do better than non-surgically treated. (3)

In summary, the salient points to consider when confronted with a heart doctor who wants to operate are:

  1. Angiograms are inaccurate and irrelevant to blood flow. This is proven by the Graboy study.
  2. The important measurement is the ejection fraction which reflects the health of the heart as a pump. A heart with an ejection fraction of 40% or greater should not be operated on.
  3. Coronary bypass surgery and angioplasty are irrelevant to your chances of survival. The CASS study of thousands of patients showed a 1.6% per year mortality in those randomly assigned to surgery and also 1.6% per year in those randomly assigned to medical management.
  4. The cardiopulmonary pump used during bypass surgery can cause brain damage in any patient. This damage can lead to memory loss, paralysis and personality change after the operation. It is estimated that 50% of patients have measurable brain damage from the effect of the use of the pump.
  5. Bypass surgery and angioplasty are not curative; they do not address the cause of vascular disease. Vascular disease in other parts of the body will progress unimpeded.
  6. Due to changes in blood flow the artery or arteries operated on progress toward reblockage at a rate ten times faster than before. This is why these procedures typically fail after a few months or years.
  7. Up to 90% of bypass operations are done with an ejection fraction of greater than 50% (i.e. on normal hearts from the pumping point of view). This means that 90% of angiograms and 90% of bypass procedures are unnecessary, at least unnecessary for the patient's health and well-being.
  8. After bypass surgery your risk of a heart attack is greater than if you are treated medically, without surgery.

Sources:

  1. Alderman EL, et al. Ten year follow-up of survival and myocardial infarction in the randomized coronary artery surgery study (CASS). Circ. 82:1629-46, 1990 CASS Principle Investigators and Their Associates: Myocardial infarction and morbidity in the coronary artery surgery study (CASS) randomized trial. New England Journal of Medicine310:750-8, 1984
  2. Graboys TD, et al. Result of second opinion program for coronary artery bypass surgery. Journal of the American Medical Association 268:2537-40, 1992
  3. Graboys TD, et al. Result of second opinion program for coronary artery bypass surgery. Journal of the American Medical Association258:1611-4, 1987
  4. Winslow CM, et al. The appropriateness of performing coronary artery bypass surgery. Journal of

Thursday, June 08, 2006

Women Bypass Patients More Likely to Die

women who have heart bypass surgery are far more likely than their male counterparts to die within days or weeks of their operation. This gender gap means many "extra" female deaths among the 270,000 Americans who have bypass surgery each year.

Now, a new University of Michigan study suggests that the answer to the mystery may lie with infections, regardless of their location in the body.

Want to read more?

New Noninvasive Imaging Technique

A study focusing on a new non-invasive imaging technology--one that may enable more precise diagnosis of coronary artery disease and treatment tailoring in individual patients--was released by Israeli researchers at SNM's 53rd Annual Meeting June 3-7 in San Diego.

"This work presents a new non-invasive cardiac imaging technology for the assessment of ischemic heart disease--also known as coronary artery or coronary heart disease--caused by the narrowing of heart arteries, which prevents blood and oxygen from reaching the heart muscle," said Zohar Keidar, deputy director of the nuclear medicine department at Rambam HealthCare Campus in Haifa, Israel. "This new modality (or technique) enables--in a single imaging session--accurate evaluation of cardiac blood vessel narrowing and blood supply to the heart muscles," said the co-author of "Assessment of Hemodynamically Significant Coronary Artery Lesions--Initial Experience With an Integrated SPECT/CT Device." He added, "These initial results suggest that this novel non-invasive imaging technology will enable more precise diagnosis of coronary artery disease, thus leading to treatment tailoring in the individual patient who may be directed to either invasive or conservative medical procedures."

Get the whole story.

Another Clean Bill of Health

Two years ago, a cardiologist in Indianapolis, attempted to scare me into having a quintuple coronary artery bypass graft (CABG). I was referred to him because I was having some rather troublesome angina pains in my chest whenever I walked as little as a few blocks. I had failed my stress test and the cardiologist said I needed a cardiac catheterization to evaluate my problem further. He warned me I might need to have a stent or two put in when he did the cath. Upon returning from the cath lab, I awoke from the twilight sleep given me to find a cardio-thoracic surgeon standing over me, along with my cardiologist.

I was told the cath showed two coronary arteries that were 100% blocked and three that were over 85% blocked. He said, that although my heart was in great shape, my arteries were terrible. I then asked a simple question the cardiologist would not or could not answer, "How can my heart be in such good shape if the arteries whose job it is to supply them with oxygen are almost totally blocked?" He simply said I needed an immediate CABG to save my life.

I sought a second opinion from a noninvasive cardiologist in San Diego named Howard Wayne. He confirmed that my arteries indeed were very bad, but told me the reason my heart was still very healthy was because other vessels, collaterals, had taken over their job and my body was also making new vessels, a process called "angiogenesis." Dr. Wayne began treating me in June 2004. I returned for followup exam a year later. I had not experienced one episode of angina since staring his medication regimen. Today, I returned from my second followup visit to Dr. Wayne. I am still angina-pain-free and his tests of my heart all came out perfectly normal.

Please, if you are told you need Bypass surgery -- Get a second opinion from a noninvasive cardiologist. You will be so glad you did. You can learn more about Dr. Wayne here.

DO YOU REALLY NEED BYPASS SURGERY? A SECOND OPINION


Dr. Wayne's newest book Do You Really Need Bypass Surgery will be available by the end of the summer or early Fall. The price of the book has not yet been determined. Some of the subject material is listed below.

You will learn from Do You Really Need Bypass Surgery:

  • That you are a victim of medical terrorism when a doctor threatens that you could have a massive heart attack or die unless you undergo immediate bypass surgery or angioplasty, and that there are no other options for treatment. Are such threats true? Almost never!
  • This book will show that the heart attack and death rate after bypass surgery is 5-10 times that of medical treatment with drugs. Bypass surgery, angioplasty and stent insertion do not prevent heart attacks or death but actually cause them.

You will learn:

  • That other complications of bypass surgery, such as brain damage and loss of memory and reasoning, occur in over one-third of patients
  • That patients undergoing bypass surgery have an accelerated progression of their coronary artery disease.
  • That symptom relief after bypass surgery is due to a dozen other reasons that have nothing to do with the bypass procedure.
  • That successful treatment of coronary artery disease with medication not only saves lives and prevents future heart attacks, but can be accomplished at a fraction of the cost of surgery and without its side effects.

Learn:

  • Why coronary artery disease is no longer the lethal disease it once was but with modern treatment with FDA approved medications has become as benign as mild arthritis.
  • Why blockage of a coronary artery may really be an adaptive mechanism on the part of the heart to protect the arterial wall downstream. Removal of that blockage may actually be the wrong thing to do!
  • Why a cardiologist trained at the Cleveland Clinic (birthplace of bypass surgery and angiograms) gave up bypass surgery in favor of medical treatment with drugs.
  • Why cardiologists continue to recommend bypass surgery even though it is obsolete.
  • Why the angiogram is not only the most inaccurate test in cardiology but the most dangerous.
  • Why the angiogram should never be used alone to diagnose and treat coronary artery disease.
  • Why the number of blocked arteries on an angiogram is irrelevant because the heart creates its own bypasses through angiogenesis and the formation of new blood vessels.
  • Why noninvasive imaging tests, at a fraction of the cost of an angiogram, and without its dangers, provide all the information necessary to diagnose and treat coronary artery disease successfully.

This book can not only save your life but the lives of your family, friends and loved ones.

Wednesday, June 07, 2006

Generx shows promise

There is a new product that shows much promise in the quest to prove CABG is not the best treatment for CAD.


Of the major interventions performed for treating severe coronary heart disease in the United States, namely percutaneous coronary intervention (PCI or angioplasty) and coronary artery bypass graft (CABG) surgeries, more than one million procedures are performed annually and more than two-thirds of these are performed on men. While angioplasty and stenting or CABG surgeries can be used to mechanically open or surgically bypass blockages of the large epicardial blood vessels that surround the myocardium, neither angioplasty nor CABG are believed to be capable of also addressing blockages or flow limitations affecting the mid-sized to smaller blood vessels which are located deeper within the heart muscle. These deeper blood vessels, which form the underlying coronary "microcirculation," are directly responsible for conveying oxygenated blood into close proximity with the adjacent heart tissue. In addition, microcirculatory impedance or resistance to flow at the downstream level can contribute substantially to reducing overall blood flow through the myocardium - which may be a contributory cause of ischemia in patients with heart disease. In that regard, many patients continue to experience angina even after surgical and other interventions have been performed to mechanically open or bypass accessible portions of the large upstream blood vessels that initially conduct blood flow into the heart.

Cardiovascular disease is also becoming the number one health problem globally. According to the World Health Organization, by 2020 heart disease and stroke will be the leading causes of death and disability worldwide, with the number of fatalities projected to increase to more than 20 million per year. Additional information regarding heart disease in both men and women can be found in the publications of the American Heart Association, including Heart Disease and Stroke Statistics, and in the reports of the World Health Organization and its affiliates.

About Generx

Generx (alferminogene tadenovec) is the lead development product in a new class of cardiovascular biologics that is being developed to leverage the body's natural healing processes in response to repeated ischemic stress (insufficient blood flow and myocardial oxygen supply due to severe coronary artery disease). The natural biologic response to repeated transient ischemia is angiogenesis, the growth of new collateral blood vessels, which is orchestrated by a complex and incompletely understood cascade involving many myocardial-derived growth factors. These newly-formed vessels can effectively augment blood flow and oxygen delivery to parts of the patient's heart downstream from a blockage in a coronary artery. In many patients however, including those with recurrent angina, coronary collateral vessel formation is insufficient to meet the heart's needs during stress. Currently available anti-anginal drugs, which may provide temporary symptomatic relief, are generally designed to alter the oxygen demand of the heart muscle or dilate vessels to relieve angina without changing the underlying medical condition.

For more information, check out http://www.pharmalive.com/News/index.cfm?articleid=346686&categoryid=40

Bypass Goof Sparks Lawsuit

Another lawsuit has been filed by the family of a patient who died after heart surgery at Mary Washington Hospital.

The suit alleges that Ralph P. Holt died because he received contaminated medicine during bypass surgery last year.

The suit was filed last week in Spotsylvania County Circuit Court and brings to eight the number of suits brought by heart patients and their survivors who believe that bacteria-laden solution caused their injuries and deaths.

The Holt case is similar to a case filed in March by the family of another man who died after heart surgery. It also resembles six other cases filed Monday in Spotsylvania court.

All involve former bypass patients at Mary Washington Hospital. The cases name as defendants Central Admixture Pharmacy Services, or CAPS, the maker of the suspect medicine; B. Braun Medical, its parent company; and MediCorp Health System, parent company of the hospital.

Holt's death was one of three cases that brought about a temporary halt to heart-bypass cases at Mary Washington. Hospital officials suspended heart surgeries in September, blaming a cardioplegia solution purchased from CAPS for a cluster of poor outcomes.

Efforts to reach CAPS representatives for comment yesterday were unsuccessful. In one court document, they blame Mary Washington for the patients' problems, saying the solution was "further prepared" at the hospital.

Hospital officials deny this, saying bacteria were discovered by independent labs in unopened bags of the cardioplegia.

After Mary Washington complained about the solution, the U.S. Food and Drug Administration did inspections and ordered the temporary closure of CAPS' Lanham, Md., plant because of bacterial contamination.

The Holts' court filing also offers a glimpse at the personal side of these cases, how a relatively healthy person can enter the hospital for surgery, only to have it take an unexpected turn.

"Obviously, he was in the hospital for surgery, but he was expecting to have a long and happy life," said Charles A. Gavin, the Richmond attorney representing the Holt family.

Holt was a 75-year-old resident of Fredericksburg, the father of one son and one daughter. He and his wife, the former Dona Grise, were within weeks of celebrating their 54th wedding anniversary.

The Holts met while attending the University of Central Arkansas in Little Rock. After graduation, he entered the Marines and served tours of duty in Okinawa, Korea and Vietnam.

After his retirement in 1981, the couple settled in the Fredericksburg area and purchased The Flower Shop in Fredericksburg. They ran the business together, with Ralph Holt doing much of the book work and deliveries, and Dona Holt specializing in floral arrangements. They sold the business in 2001.

Afterward, the couple enjoyed traveling, something they had done frequently while he was a Marine.

"Ten days prior to his surgery, they were in Colorado," Gavin said.

They also enjoyed golf, playing together three or four times a week. A dream for both was to attend the Masters golf tournament in Augusta, Ga. Each year they tried unsuccessfully to purchase tickets. They were able to get tickets for the 2006 tournament.

Friends describe Holt as a vigorous man who exercised regularly and appeared younger than his years. His widow's lawsuit describes him as "in general good health, fully independent, active and loved by his family."

But he experienced a "spell" at church one day and went for a cardiac catheterization at Mary Washington on Aug. 16. The test revealed a blockage, and his physician recommended coronary artery bypass graft surgery.

Dr. John M. Armitage performed the surgery on Aug. 31.

During the surgery Armitage used a cardioplegia solution manufactured by CAPS in Lanham where the suspect material was made.

Cardioplegia is a mixture of chemical compounds routinely used during open-heart surgery to still the beating heart. It comes in a three-bag set and is administered intravenously throughout the surgery.

Holt never recovered from the bypass surgery. His blood pressure plummeted, and he bled internally. Eventually his kidneys failed. The constellation of symptoms is called systemic inflammatory response syndrome.

Armitage decided to reopen Holt's chest two days later, but his condition worsened throughout the day.

"They couldn't figure out what was going on," Gavin said.

Holt died that evening, Sept. 2.

Friends joined the family for the funeral at Fredericksburg United Methodist Church. Holt was buried at Quantico National Cemetery.

Dona Holt didn't attend the Masters tournament in April, Gavin said, and she has not played golf since her husband's death.


Saturday, June 03, 2006

Study says do not underestimate the pain factor


The results of a study published in the Journal of Thoracic and Cardiac Surgery shows postoperative pain in patients who have had CABG surgery is significant.

Prevalence, characteristics, and predictors of chronic nonanginal postoperative pain after a cardiac operation: A cross-sectional study

  • Nonanginal chronic postoperative pain affected 23% of patients.

  • Eighty percent of them had pain 1 or more days per week.

  • The worst and usual pain intensities during the week preceding the survey reached moderate to severe levels (≥4/10) in more than half of the patients.

  • Thirty-one percent of the patients with chronic postoperative pain had taken analgesic pain medication during that week.

  • During the same period, pain interfered significantly (≥4/10) with various aspects of patients' daily life (eg, general activity level: 39.1%, sleep: 36.7%).

  • When patients with and without chronic postoperative pain were compared, the former group had significantly higher levels of anxiety and depression, and they perceived their health-related quality of life as more compromised.

  • Multivariate logistic regression analysis revealed that greater analgesic needs in the first few days postoperatively were associated with an increased risk of chronic postoperative pain.

  • The only other significant factor was the time elapsed from surgical intervention to survey: the longer it was, the less likely the patients were to report chronic postoperative pain.

CONCLUSION: The prevalence, severity, and effect of chronic postoperative pain after cardiac surgery should not be underestimated. Longitudinal prospective studies are needed to further evaluate risk factors, including inadequate postoperative pain relief in the acute period.


Friday, June 02, 2006

CABG Makes Many Lose Their Minds, at least for a while

As many as 90 percent of patients who undergoCoronary Artery Bypass Graft Surgery, experience Mild Cognitive Impairment afterwards. This condition, which also is the pre sequellar to Alzheimer's Diseases, persists in as many as 24 percent of them. Allon Therapeutics, Inc. thinks they may be onto a treatment for this side effect of CABG surgery.

Allon Therapeutics Inc. (TSX:NPC), The Neuro Protection CompanyTM, today announced that patient enrolment has begun for a Phase II human clinical trial evaluating the Company's product AL-208 as a treatment for the mild cognitive impairment (MCI) that commonly occurs following coronary artery bypass graft (CABG) surgery.

Gordon McCauley, President and CEO of Allon, said the Phase II trial will evaluate the safety and effectiveness of AL-208 at preventing or reducing MCI in CABG surgery patients aged 65 to 79. Preventing or reducing MCI post-CABG has a potential market estimated at US$500-million for which there is no available treatment today.

"This clinical trial is particularly significant for Allon because it is the first trial that will evaluate the effectiveness of one of our drugs in patients," McCauley said. "We believe this will be the first of several human clinical trials starting in the next year to evaluate the effectiveness of our drugs in different neurodegenerative diseases and conditions."

The initial portion of the study in which all patients receive AL-208 will be open-label to confirm safety, followed by a randomized placebo-controlled portion. In total, approximately 200 patients will be treated with AL-208 (or placebo) during surgery. The patients will be assessed using standard cognitive tests, administered several weeks after surgery, to determine the impact on cognitive function of patients treated with AL-208 versus patients in the control group. The trial will be conducted in approximately 20 hospitals in the US and Canada.

The Company expects results of the Phase II trial will be released during the second half of 2007.

Allon's compounds have been shown to be effective in preventing and repairing brain cells from disease or injury in 14 different pre-clinical animal models of eight central nervous system conditions. In some acute animal models, a single administration of AL-208 has provided 30 days of neuroprotection and maintenance of cognitive function after a single administration.

About MCI-post CABG

Mild cognitive impairment is a common result after coronary artery bypass graft surgery (CABG - commonly known as "bypass surgery").

Some studies estimate that cognitive impairment occurs in 90% of cases in the first week post-surgery, that more than 50% of patients show impairment when discharged from the hospital, and that 24% continue to show impairment after six months.

Approximately 500,000 patients in the United States and 800,000 patients worldwide undergo coronary artery bypass graft surgery every year. Currently there is no therapy available that ameliorates or treats the cognitive damage associated with artery bypass surgery.

About Allon

Allon Therapeutics Inc. is a Canadian biotechnology company developing drugs that protect against neurodegenerative conditions such as Alzheimer's disease, mild cognitive impairment, stroke, traumatic brain injury, multiple sclerosis and neuropathy. The Company is listed on the Toronto Stock Exchange under the trading symbol "NPC" (Neuro Protection Company) and based in Vancouver.

Tuesday, May 30, 2006

Cardiologists Lose License, should be in Prison

This story is from the Redding, CA Record Searchlight

by Ryan Sabalow

After almost four years of investigation, the state medical board moved Tuesday to revoke or suspend the license of a Redding doctor accused of having performed hundreds of unnecessary heart procedures.

In an accusation filed with California Attorney General Bill Lockyer, Dr. Fidel Realyvasquez Jr. is charged by the Medical Board of California with gross negligence stemming from bypass surgeries he performed on three patients in 2001 and 2002.

According to the accusation, Realyvasquez, the chief cardiac surgeon at what was then Redding Medical Center, operated on the patients -- ages 58, 52 and 76 -- without cause, based solely on diagnoses made by cardiology chief Dr. Chae Hyun Moon.

Moon, who also is under investigation by the state medical board, voluntarily agreed to stop practicing medicine in July 2003.

Moon, 58, is charged by the medical board with dozens of counts of gross negligence, incompetence, dishonesty and corruption, filing false or fraudulent claims, failure to maintain adequate records, and repeated negligent acts.

That investigation is ongoing.

Tuesday's accusation is that Realyvasquez, 57, performed the three coronary bypasses without verifying Moon's diagnoses.

The medical board's accusation reports each of the three surgeries in detail, using words like "failed to," "unnecessary" and "erroneous" to describe Moon's diagnoses and the following surgeries by Realyvasquez.

The accusations identified the patients by initials to protect their privacy.

In the case of the of the 58-year-old patient, identified as "E.G.," Realyvasquez performed a triple bypass coronary graft without checking to see that the patient could have been helped by a less invasive procedure, according to the filing.

In the second case, Moon told a 52-year-old woman in March 2002 she needed a coronary artery bypass graft surgery, the filing says. Moon suggested that if she didn't get one, "her grandchildren might find her dead," according to the accusation.

The accusation calls Moon's diagnosis of heart angiography a "misinterpretation" and says the patient had only "minor, if any, coronary artery disease."

In his examination of the patient, "Dr. Realyvasquez simply restated Dr. Moon's findings ... and obtained the patient's consent for the surgery," according the accusation.

The most serious allegation stems from the 76-year-old woman's surgery.

The accusation says she "suffered a major embolic stroke, from which she has not yet fully recovered" because of a four-vessel bypass Realyvasquez performed based on Moon's diagnosis.

Realyvasquez's Sacramento attorney, Malcolm Segal, said the medical board's claims are unfounded because his client simply was going off of test results given to him by another physician -- something every surgeon does.

"What (the accusation) seems to be saying is that no physician can rely upon any test report prepared by another physician on the case," Segal said. "I question then, does that mean that a surgeon has to repeat and personally do all the blood tests, repeat and personally do all the X-rays, repeat and redo every other test, even when, by training, that's not his responsibility?"

Saying that he had not seen the medical board's accusations, Moon's attorney, Matthew Jacobs of Sacramento, declined to comment on the allegations against Realyvasquez or Segal's statements.

Redding attorney Russell Reiner, who represents 345 patients who sued the doctors in civil court, said the final decision lies with the person holding the scalpel.

"It's the surgeon's ultimate responsibility to determine whether a person proceeds to surgery," Reiner said. "Realyvasquez failed in his responsibility."

Reiner said the medical board's accusation is "long overdue."

The complaint urges that Realyvasquez's license be revoked or suspended, and that he be forced to pay the costs of the investigation, future enforcement and probation.

Tuesday's filing is the latest chapter of the Redding Medical Center saga, which began in October 2002, when federal agents raided the hospital after tips from whistle-blowers.

Federal officials have been hashing out a settlement in that case since Nov. 15, when Moon and Realyvasquez came to a "global settlement" and agreed to pay prosecutors $1.4 million each.

A spokeswoman for the U.S. attorney's office in Sacramento said prosecutors have until June 2 to finalize that deal.

The settlement ended three years of criminal investigation.

No criminal charges were filed, and none of the doctors has admitted guilt.

In February, Realyvasquez and two other surgeons, Kent Brusett and Ricardo Javier Moreno-Cabral, were ordered to begin paying a $21 million civil settlement to 760 patients.

Moon and other cardiologists settled separate civil suits for $24 million nearly a year earlier.

Both doctors still live in Redding, their attorneys said.

Segal said his client has been "working on other matters related to medicine, including research."

Reporter Ryan Sabalow can be reached at 225-8344 or at rsabalow@redding.com.


Thursday, May 25, 2006

CABG - Legal Assault with a Deadly Weapon.

If a patient is told by a cardiologist that his or her heart is in "GREAT SHAPE," but he or she needs a CABG or he could drop dead at any time, and the doctor hands the patient a pen with which to sign the permission to perform the surgery, he should be arrested and charged with conspiracy to commit assault. If this patient, with the heart in "GREAT SHAPE," indeed has the surgery, the cardio-thoracic surgeon and all of his assistants, including the cardiologist who referred the patient should be arrested for assault with a deadly weapon. And if, this patient whose heart was in "GREAT SHAPE" before the surgery happens to die on the table or of later complications, that entire group of conspirators should be charged with murder.

Two years ago, after seeking a second opinion from a noninvasive cardiologist, I opted for treatment with medication for my unstable angina instead of a quintuple bypass. Ten days ago, my friend underwent a triple CABG and he is miserable. He is afraid to go to sleep at night for fear that he won't wake up. He is not allowed to lift anything heavier than his shoes for several months. He can't walk more than 1/2 hour a day for 3 months. He feels like his guts are going to fall out.

Granted, a year from today, if he is lucky, he'll say to me, "I feel great, I am so glad I had that surgery last May." But I am equally convinced I'll be able to say, "I've felt great for three years and didn't have the CABG." He may then say, but you must take all kinds of medicine every day for the rest of your life." And my response shall be, "Well, don't you as well."

Before you let a cardiologist talk you into this major surgery that you probably don't need, please, get a second opinion from a noninvasive cardiologist. If your current heart doctor says, "Oh, you are a walking time bomb, you haven't time for that," or "Dr. Cutter is a cardio-thoracic surgeon, he's your second opinion," RUN, don't walk to a noninvasive cardiologist because chances are those other two guys are lying to you.

Wednesday, May 17, 2006

Some Disturbing Facts

The fact that most patients with Coronary Artery Disease (CAD) can be safely and medically treated instead of with invasive and surgical solutions such as angioplasty and Coronary Bypass Arterial Grafts (CABG) has been known for over ten years. C. Pepini, writing in the Journal of Myocardial Ischemia in 1995 said this in his paper titled "Management of Myocardial Ischemia: A Time to Re-evaluate." In 1997, in their paper Evidence-Based Coronary Care," in a 1997 Annals of Internal Medicine , Braunwald and Antman reaffirmed Pepini's findings.

My own noninvasive cardiologist, Howard Wayne, MD (www.heartprotect.com) says in more than 22 years of treating his CAD patients with medication, only 11 of them had to have a CABG because they stopped responding to his medical regimen. During the same period, mortality in his patients from CAD and incidences of heart attacks has been less than one percent a year.

Finally, Dr. Thomas Preston, MD, a Professor of Medicine at the University of Washington School of Medicine and Chief of Cardiology at Pacific Medical Center in Seattle, said, "CABG is overused, frequently ineffective, and absurdly expensive. It is the epitome of modern medical technology, yet, as it is now practiced, its net effect on the nation's health is probably negative." Strong words from a cardiologist, but no stronger than those Howard Wayne has been saying for years.

In his editorial, "Marketing an Operation," Preston states the following:
  • CABG consumes more medical money than any other treatment of procedure.
  • Although performed less frequently than most common abdominal and gynecological operations, it is the leader in terms of equipment and personnel, hospital space, and assorted resources.
  • CABG does not cure CAD, is scandalously overused, and its high costs drains resources from other areas of need.
  • Fully half (Wayne says 95%) of the CABGs done in the United States are unnecessary surgeries that do not save lives or even prevent heart attacks.
  • Among sufferers of CAD, those treated without surgery enjoy the same survival rate as those who do.

These are the words of a respected Professor of Medicine and a chief of Cardiology for a major medical center. They are the words of a noted noninvasive cardiologist who has been treating CAD patients primarily with medication for over 22 years. There has been reams of papers published in medical journals for more than a decade that expose the Coronary Artery Bypass Graft as unnecessary, expensive and dangerous. They stop your heart when they perform this surgery for crying out loud. Listen to the wisdom of a few upstanding cardiologists who are desperately trying to stop the gross over-prescribing of CABGs.

Why do cardiologists insist on performing this surgery instead of treating their CAD patients? There can only be two answers to this question. They either do not know any better or it is a matter of they put their own financial well-being ahead of the health of their patients.

This message is being sent out in emails and placed on message boards and forums around the Internet. Administrators of these sights have a choice. They can continue deleting these posts and demonstrate they are part of the problem, or they can prominently display and promote this discussion. Let's see what side of the issue they are really on.

Thursday, May 11, 2006

It is high time for an update

Hey, Dr. Corey, I'm still alive and kicking. In fact, two years after refusing to have my chest cracked open by a cardio-thoracic surgeon at Indiana Heart Hospital, I am feeling better than ever! This despite the scare tactics you and he used to try to get me on the operating room table. It turns out I was not the walking time bomb you said I was.

In fact, I am alive and well, working on an offshore drilling rig in Nigeria, West Africa. I am sitting on that rig this very moment, typing this post to the blog that I have not posted on in nearly a year. I just got off the phone with my lovely wife, Rebecca (YES! I've gotten married since my last post! -- and she's 16 years younger than I) and she gave me the sad news that a friend of ours is trying to be talked into a triple cardiac artery bypass graft.

It seems our friend has symptoms that are similar to mine and a story that practically mirrors mine. He has angina. His doctors tell him that his coronary arteries are badly blocked -- but his heart is in good shape. Well people!! If the heart is in great shape, it must be getting oxygen, that's what keeps the heart in great shape! If the oxygen isn't getting through the clogged coronary arteries, it must be bypassing them in some way, right?

The body is a miraculous entity. It has the capability to heal itself. When arteries get blocked, the ingenious body builds natural bypasses to replace the clogged ones. There is a doctor in San Diego named Howard Wayne. He taught me this fact and has been treating me for two years with medication. MEDICATION!!! Not surgery. I didn't get cut open. I didn't have my heart stopped, I didn't have a long post-op recovery period and an even longer period of physical therapy AND, I didn't put a lot of money in my surgeon's pocket!

Dr. Wayne is a board certified cardiologist, among other certifications he can boast. He is not a quack. He costs about 10 percent what bypass surgery charges insurance companies. He is not trying to pay for his Mercedes Benz 500 or the new olympic swimming pool in his backyard. He is trying to show the 80,000 Americans doctors scare into bypass surgery every year that for most of them, not only is the surgery unnecessary, it reduces your life expectancy! You could do nothing at allfor your angina and still live longer than many bypass victims.

Yes, I wrote "VICTIMS." Most patients who undergo bypass surgery are victims of scare tactics made by cardiologists who either do not know what they are talking about, or worse, are purposely misleading their patients to get them to have unnecessary but very expensive surgery.

I am going to call my friend this afternoon at 3 pm Nigeria time (10 am Indianapolis time) and ask him to please read my blog. I'll ask him to go to the archives and start at the beginning. I also want to encourage him to call Dr. Wayne in San Diego. I have an appointment on June 6 to see him for my second annual check up.

Wake up America! Your cardiologist is more interested in his financial well being than your health.

Wednesday, September 07, 2005

So Long Gilligan

Bob Denver died this week. The 70-year old comedic actor was best known for his portrayal of Gilligan of Gilligan's Island. He succumbed to complications from a coronary artery bypass surgeons convinced him he needed. One has to wonder if, like Bill Clinton, he did not receieve a second opinion from a noninvasive cardiologist. You only hear about the failures of bypass surgery when someone famous passes that has undergone one. But there are thousands of bypasses performed unnecessarily year after year to keep big hospital corporations solvent and highly paid surgeons able to buy a brand new Mercedes Benz every year.

It has been nearly two years since my cardiologist attempted to coerce me into getting a quintuple coronary artery bypass. I began being treated with medication on June 6, 2004 and I feel great. And I don't have a nasty scar on my chest where the surgeons cracked it open. Already I have lived longer than the doctors at the Indiana Heart Hospital thought I would and I am going strong.

I have been working as a safety advisor on an offshore drilling rig in Nigeria, West Africa since April. I feel strong and vital and my stamina is that of a man ten years younger than I am. If I had the surgery, chances are I would still be experiencing post operative pains and complications and wouldn't feel half as good as I do now.

In November, Rebecca and I are going on a five night vacation to the City of Lights, Paris, France. I fully intend to take advantage of the romantic atmosphere and environment and enjoy myself with the woman I love.

If doctors tell you or a friend you need a bypass, politely tell them you want to obtain a second opinion froma noninvasive cardiologist. Try medication before getting your chest cracked open unnecessarily.

Friday, June 03, 2005

I Am Getting Better!!

Rebecca and I journeyed to San Diego on May 28 and returned on June 1. It was my annual pilgrimage to Dr. Howard Wayne's Noninvasive Heart Clinic. My appointment was on May 31 and we enjoyed and appreciated the hospitality and fellowship of friends who live in that beautiful city. In fact, they kindly loaned us a car while we were there.

Enough about the non-medical stuff -- Let's get to the reason for this post:

I have spent the past year taking medication twice a day for a problem cardiologists in Indiana insisted must be corrected with a Quintuple Coronary Artery Bypass Graft. I was warned that unless I had the surgery immediately, I faced the probability of having a heart attack within three months or less.

Well, I am still standing! I fact, according to Dr. Wayne, my heart is in better shape today than it was when he saw me exactly a year ago. The walls of my left atriumthat were slightly enlarged have decreased in size. My ejection fraction has gone from 65 to 72.

And I haven't experienced angina symptoms since I began his regimen, so he has removed Unstable Angina from my list of diagnoses.

But by far the best news I have to report, is I started working again. That's right, after almost two years on Social Security Disability, I felt good enough to work and was offered employment.

I began working as a Safety Advisor to ExxonMobil on the drilling rig Scarabeo 7, working off the coast of Nigeria, West Africa. I spent 43 days on the rig recently, my first hitch offshore since 1998.

Dr. Wayne was opposed to the job at first, since I would be so isolated from a decent medical facility. But everything went well and he has certified me "fit for duty."

I return to Nigeria on July 4.

Remember: IF YOUR DOCTOR INSISTS YOU NEED CORONARY BYPASS SURGERY -- GET A SECOND OPINION FROM A NONINNTERVENTIONALIST CARDIOLOGIST.

Wednesday, March 23, 2005

California Here I Come

Well, this June will mark a year of treating my coronary artery disease and hypertension with Dr. Wayne's medical regimen. I am so grateful I decided to get a second opinion when in May of 2004, I was told by a cardiologist and cardiothoracic surgeon at Indiana Heart Hospital that I needed an immediate quintuple coronary artery bypass graft (CABG). Instead of getting my chest cracked open and the trauma of dangerous, potentially life-taking major surgery and spending months in rehab trying to recover from unnecessary surgery, I have had a productive, active and satisfactory life.

My blood pressure runs between 88/56 and 100/62 while at rest. Side effects from this lower than normal BP are few and very transient. I have experienced exactly one episode of angina that lasted approximately ten minutes and stopped about five minutes after I began resting during a brisk walk in cold weather. I have had absolutely no shortness of breath or other symptoms since before June 6 2004.

I am returning to San Diego on June 29 for a follow-up appointent with Dr. Wayne. I am looking forward to seeing this man who literally let me live the good life.